

Expert articles, clinical developments, and innovation trends in orthopedic implants and trauma fixation.
In-depth coverage on biocompatible materials, implant engineering, and modern surgical techniques.
Choosing an External Fixator in 2026 requires more than comparing frame designs or counting available components. The correct choice depends on fracture pattern, soft-tissue condition, bone quality, patient mobility, and surgical objectives. A frame standing beside the operating table may look efficient, yet its real value appears around the patient’s leg, pin sites, and daily routine.
Dr. Gavriil A. Ilizarov, the pioneer of modern circular fixation, stated, “The tension-stress effect is a biological law that governs the regeneration of tissues.” His principle still influences contemporary External Fixator planning. Modern systems now offer lighter materials, computer-assisted alignment, improved clamps, and patient-specific configurations. However, technology cannot replace clinical judgment. A surgeon must assess safe corridors, neurovascular risks, expected loading, and the patient’s ability to manage cleaning and follow-up care.
This guide examines how to compare circular, unilateral, hybrid, and computer-assisted frames. It considers stability, adjustability, radiographic access, comfort, assembly time, and long-term maintenance. It also asks an uncomfortable question: is the most advanced frame always the best option? Usually, no. A simpler construct may provide safer handling and clearer instructions. Conversely, a complex deformity may require precise multiplanar control. No checklist is flawless. Swelling can change, compliance can disappoint, and a technically elegant frame can become impractical at home. Reliable selection therefore combines published evidence, experienced surgical assessment, manufacturer instructions, and honest discussion with the patient. In 2026, the best External Fixator is not merely innovative. It is appropriate, measurable, and manageable.
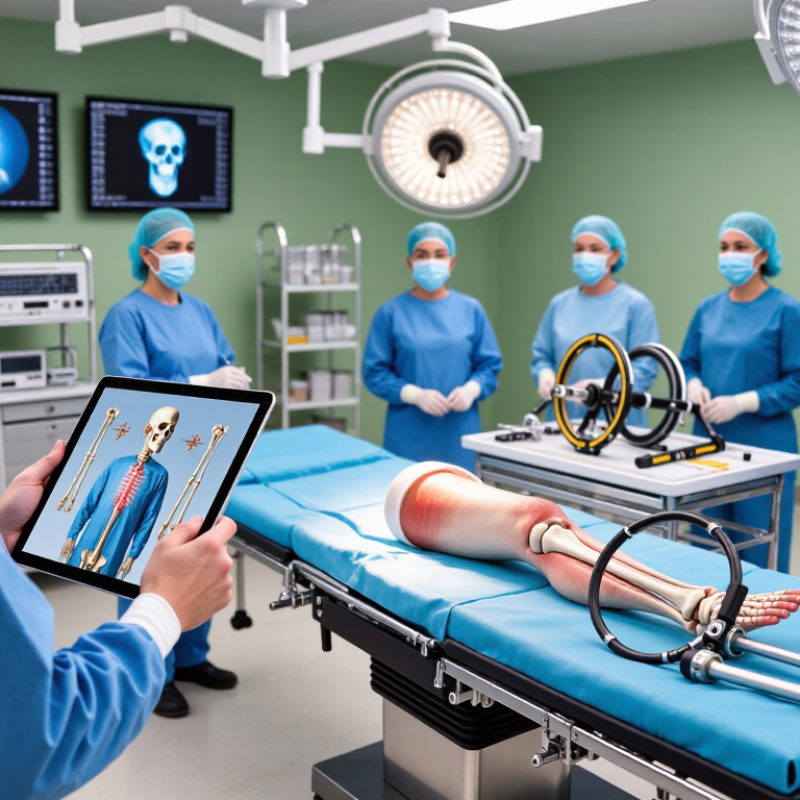
An external fixator is a stabilizing frame positioned outside the body. Pins or wires pass through the skin and connect injured bone to this frame. The device helps maintain alignment while swelling, wounds, or infection make internal fixation unsuitable. It can support open fractures, severe soft-tissue injuries, temporary damage control, and selected limb-lengthening procedures.
Clinical decisions should match the injury, bone quality, skin condition, and patient’s overall health. A modular frame may allow later adjustment as swelling decreases or surgery progresses. Surgeons also consider pin placement, joint movement, imaging access, and the patient’s ability to manage daily care. Neurovascular checks remain essential. So does regular assessment of pin sites, pain, drainage, and frame stability. The frame is not a cure. It is a controlled mechanical solution.
Tips: Ask how long the frame may remain in place. Confirm cleaning instructions before leaving the hospital. Keep dressings dry unless the clinical team advises otherwise. Report increasing redness, fever, loose pins, numbness, or sudden pain promptly. Small details matter.
The best choice is not always the most complex one. A lighter frame may improve mobility, yet a stronger construct could be safer for unstable injuries. This balance requires examination, imaging, surgical experience, and honest follow-up discussions. Clinical practice is still imperfect, especially when swelling changes quickly. Reassessment may reveal that the original plan needs revision.
Choosing an external fixator starts with the patient, not the device. The assessment should include age, bone quality, skin condition, circulation, nerve function, and overall health. Diabetes, smoking, poor nutrition, or reduced immune function may affect healing and pin-site care. Can the patient understand cleaning instructions? Can they return for follow-up? These questions matter.
The injury needs equal attention. Review imaging for fracture location, bone loss, joint involvement, and alignment. Examine swelling, wounds, contamination, and soft-tissue damage. Severe swelling may favor temporary stabilization before definitive treatment. Pin placement should protect healthy tissue and avoid planned surgical approaches. The frame must provide enough stability without blocking wound care, imaging, or movement of nearby joints.
Fit matters. So does adjustability.
In practice, the safest choice often changes after swelling decreases or new imaging becomes available. A frame that looks suitable in the operating room may become restrictive during rehabilitation. This is an easy detail to miss. Clinicians should reassess fixation stability, pain, skin tension, pin sites, and patient tolerance at every review. Selection should follow current orthopedic guidance, local protocols, and the judgment of a qualified trauma team. The patient’s ability to manage daily care deserves the same attention as the fracture pattern.
How to Choose an External Fixator in 2026?
External fixator selection should begin with the fracture pattern, soft-tissue condition, and treatment goal. Unilateral frames are often lighter and easier to adjust. Circular frames can provide strong multiplanar control around complex deformities. Hybrid designs may balance ring stability with easier access to injured skin. The choice is not purely mechanical. Patient comfort, swelling, bone quality, and expected rehabilitation also matter.
Compare each component carefully. Pins need suitable diameter, safe corridors, and adequate spacing. Fine wires can improve fixation in small fragments, but they may complicate soft-tissue care. Rods and rings should resist bending without creating unnecessary weight. Clamps must permit controlled adjustments and remain secure during movement. Hinges are useful when gradual correction or joint motion is planned. A common planning mistake is choosing a strong frame that blocks wound access. Strength alone is not enough. I have also seen teams underestimate how difficult daily cleaning becomes around crowded connectors.
Tips: Sketch the frame before surgery. Check pin paths against imaging and future incisions. Leave room for dressings, swelling, and emergency access. Ask whether the patient can manage the frame at home. Test adjustment steps with the clinical team. Document torque settings and follow-up measurements. Small differences in component placement can affect alignment, comfort, and stability. Reassess the design when swelling changes, because the best frame on day one may need revision later.
Pin diameter is selected according to the anatomical site, available bone stock, soft-tissue conditions, and the required frame stiffness. The ranges shown are typical clinical ranges for Schanz-type half-pins and are intended for educational comparison rather than patient-specific treatment decisions.
Unilateral frames are generally lightweight and quick to apply; bilateral or biplanar frames can increase multiplanar stability; circular and hybrid frames provide adaptable fixation around complex fractures, periarticular injuries, and limited soft-tissue envelopes. Final selection should follow fracture pattern, bone quality, soft-tissue status, and the surgeon’s technique.
Begin with the injury, not the device catalogue. Review radiographs and, when necessary, CT images to define fracture geometry, bone loss, and joint involvement. Examine swelling, wounds, circulation, nerve function, and skin condition. A temporary frame may suit severe swelling, contamination, or uncertain soft-tissue viability. A definitive frame may support gradual correction, lengthening, or complex reconstruction.
Match the frame to the clinical goal. Ring systems can offer adjustable, multiplanar control. Monolateral systems may provide faster application and easier access to wounds. Hybrid constructs can balance stability with practical surgical access. Pin diameter, safe corridors, working length, and expected loading deserve careful planning.
Small details matter. A frame that looks strong can still fail if pins sit in poor bone or restrict essential movement.
Patient factors shape the decision. Consider age, bone quality, mobility, wound care ability, and access to follow-up imaging.
Discuss pain, cleaning, sleep, work, and possible reoperations honestly. Evidence-based guidance helps, but it cannot replace trained clinical judgment. Multidisciplinary review is valuable for open injuries and medically complex patients.
I would not assume the most adjustable system is always the best choice. Simplicity may improve adherence, yet my initial plan can change after swelling decreases or new imaging appears.
Document the reasoning, reassess alignment regularly, and modify the construct when the patient’s condition changes.
Safety begins with the patient, not the frame. Choose a system that allows stable fixation, clear wound access, and simple adjustments. A 2024 WHO Global Patient Safety Report estimates that one in ten patients experiences harm during healthcare. More than half of this harm is considered preventable. That statistic should influence every fixation decision.
Monitoring must be practical at the bedside. Look for visible pin sites, measurable alignment, and components that remain accessible after swelling changes. Record pain, drainage, skin tension, neurovascular findings, and frame stability at each review. Infection risk varies widely across studies, but published orthopedic reviews commonly report pin-site problems in 10% to 40% of cases. Do not treat that range as a prediction. Patient factors change it.
Think beyond the first operation. A frame may need staged correction, dynamization, or conversion after soft-tissue recovery. Plan for those possibilities before tightening every clamp. Small radiographic changes can matter. A 2023 international patient-safety review also emphasized structured handovers and documented reassessment for reducing avoidable device-related errors. In practice, I still see monitoring plans written too vaguely. “Review regularly” is not enough. Specify who checks the frame, when imaging occurs, and what finding triggers adjustment. No checklist replaces judgment. Yet no judgment should operate without a checklist.
It is a frame outside the body. Pins or wires connect the frame to the injured bone. It helps maintain alignment when internal fixation is unsuitable.
It may support open fractures, severe swelling, soft-tissue injuries, or temporary damage control. It can also assist selected limb-lengthening procedures. The frame is not a cure.
They review the fracture, bone quality, skin, circulation, nerve function, and general health. Imaging shows bone loss, joint involvement, and alignment. The simplest suitable frame may be safer.
Ring systems can provide adjustable, multiplanar control. Monolateral systems may allow faster application and easier wound access. Hybrid designs can balance stability with practical care.
Severe swelling may require temporary stabilization before definitive treatment. The frame may need adjustment after swelling decreases. The first plan can be wrong.
The patient should understand cleaning instructions and attend follow-up visits. Mobility, sleep, work, nutrition, and wound-care ability also matter. Follow-up access matters.
Keep dressings dry unless the clinical team gives different instructions. Watch for increasing redness, fever, drainage, loose pins, numbness, or sudden pain. Report changes promptly.
It can limit nearby joint movement if positioned poorly. Clinicians plan pin locations and frame size carefully. Rehabilitation needs regular reassessment. Fit matters.
Yes, the construct may be adjusted when swelling, alignment, pain, or healing changes. New imaging can alter the plan. Clinical practice is not perfect.
Choosing an External Fixator in 2026 requires a structured evaluation of the patient, injury, and treatment objectives. External fixators provide temporary or definitive stabilization by connecting bone pins or wires to an external frame, helping manage fractures, soft-tissue injuries, deformities, and situations where internal fixation may not be suitable. Selection should consider fracture location and complexity, bone quality, soft-tissue condition, infection risk, patient age, mobility, and the need for future procedures. Different frame designs, including unilateral, circular, hybrid, and modular systems, offer varying levels of stability, flexibility, and access to injured tissues.
A suitable system should be chosen step by step: define the clinical goal, assess the anatomy and soft tissues, select appropriate pins or wires, determine frame configuration, and confirm stability without restricting necessary movement or wound care. Safety depends on accurate placement, pin-site hygiene, regular imaging, neurovascular checks, and monitoring for loosening, infection, alignment changes, or discomfort. The best choice should also allow adjustment, gradual correction, or frame removal as healing progresses, supported by continuous clinical reassessment.
